
04 December 2025
Why acid reflux can continue despite medication, the three tests that decide whether surgery is right for you, and why I prefer a Toupet fundoplication, from a UK-trained Consultant General Surgeon at Fakeeh University Hospital, Dubai Silicon Oasis.
By Dr. Appou Tamijmarane | MBBS, MS (Gen Surg), FRCS (Edinburgh), FRCS (Glasgow), FRCS (Gen Surg), CCT
Consultant General Surgeon specialising in HPB, Upper GI, and Advanced Laparoscopic Surgery
Fakeeh University Hospital, Dubai Silicon Oasis | DHA License No: 50530660-001
Published: 4 December 2025 | Last reviewed: November 2026 | Reading time: 8 minutes
Written for people in Dubai who still have acid reflux despite medication and want to understand their next options.
Signs PPIs are not working · The surgical evaluation · What tests might find · Why Toupet · After failed surgery · Book a consultation · FAQs
Key Takeaways
Proton pump inhibitors (PPIs) such as omeprazole control acid reflux for most people. When they stop working, the next step is testing, not a higher dose. Dr. Appou Tamijmarane, Consultant General Surgeon, assesses reflux that no longer responds to medication at Fakeeh University Hospital, Dubai Silicon Oasis.
For many people with acid reflux (GERD or GORD), a PPI such as omeprazole works well. But every week in my clinic at Fakeeh University Hospital, I see patients who have taken PPIs for months or years and still have acid reflux despite medication: night-time reflux, regurgitation, a cough that will not settle, and symptoms that return as soon as they reduce the dose.
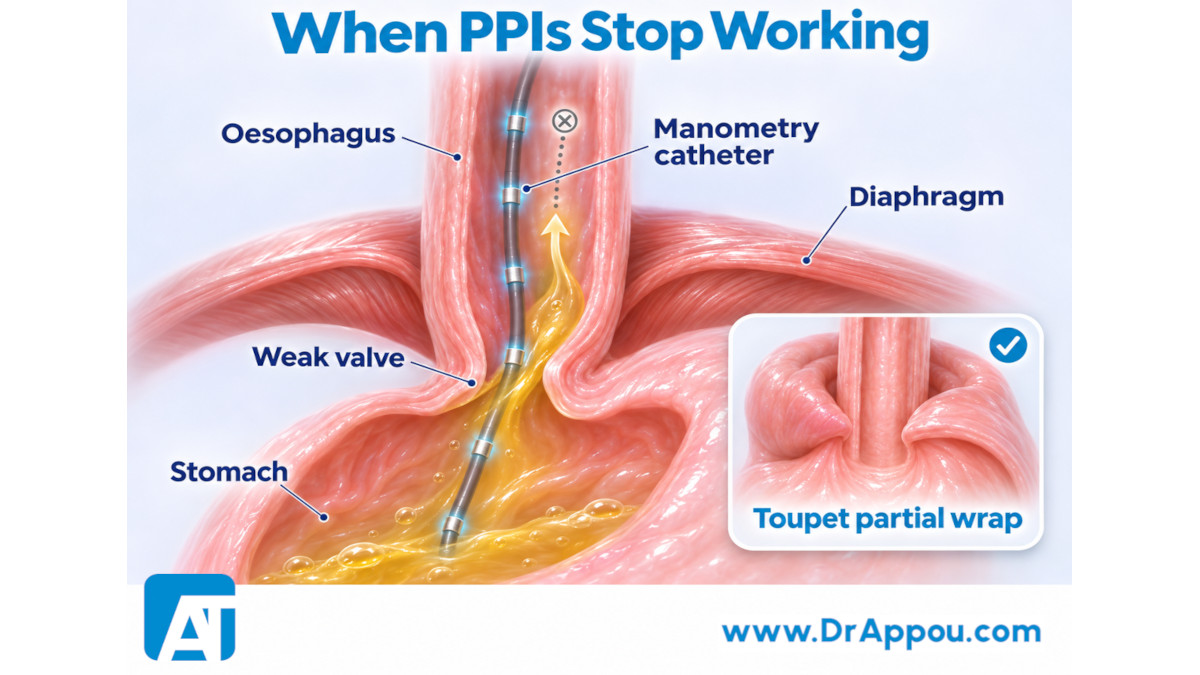
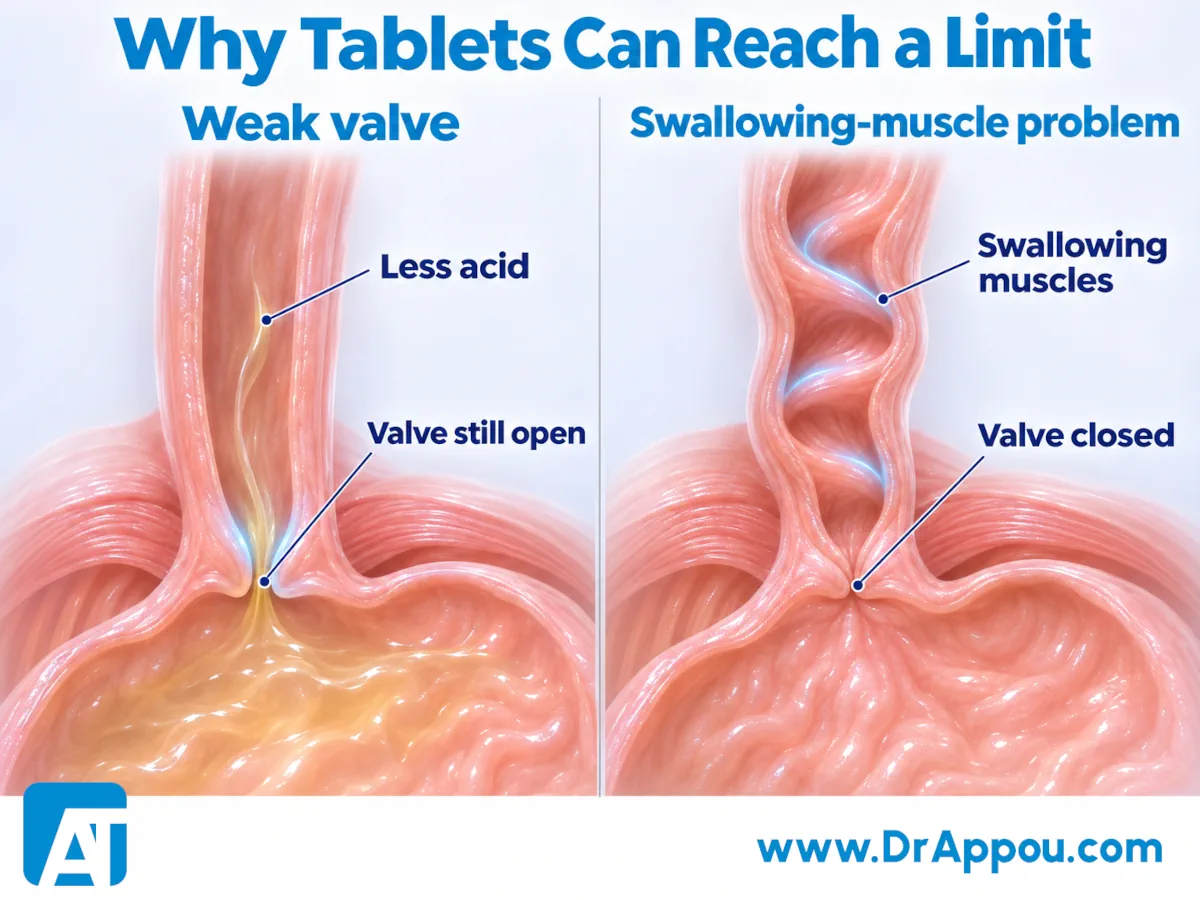
There are usually two reasons. The first is mechanical: PPIs reduce acid, but they do not repair a weak valve at the bottom of the oesophagus (the lower oesophageal sphincter), often made worse by a hiatal hernia. The second is less well recognised: in some patients, the symptoms come from a disorder of how the oesophagus moves, which can look very like reflux and only shows up on specialist testing. This matters greatly for anyone considering surgery.
For more detailed information on reflux, GERD and hiatus hernia, read my Acid Reflux, GERD and Hiatus Hernia guide.
On this page
Reflux at night, regurgitation, a lasting cough, or needing ever-higher doses all suggest a problem that tablets alone may not solve.
These are the patterns I hear most often, and any one of them is a good reason for a specialist review:

They usually mean the problem is structural, or not reflux at all, rather than the wrong medicine. First, check the timing: PPIs work best taken 30 to 60 minutes before a meal, not with it or at bedtime. [1] Long-term PPIs are reasonable when there is a clear reason for them, but they should be reviewed regularly with your doctor. [8]
“Sometimes patients may be self-medicating for a long time with acid-reducing medications, such as omeprazole, and they may insist that they don’t need any further investigation. From my personal experience, if your symptoms continue to last beyond 4 to 6 weeks despite taking medications, then you need to be investigated, particularly by an endoscopy.”
Dr. Appou Tamijmarane
See a surgeon or gastroenterologist urgently if reflux comes with:
Go to an emergency department if you vomit blood or pass black, tarry stools. If you have new, severe or crushing chest pain, call 998 first: reflux can feel like heart pain, so the heart must be checked before reflux is considered.
A consultation with me does not begin with a recommendation for surgery. It begins with three tests: an endoscopy, pH monitoring and manometry.
I need an objective picture of your oesophagus, not just your symptoms. Dubai’s reflux guidance and the main international guidelines follow the same order. [2][3]
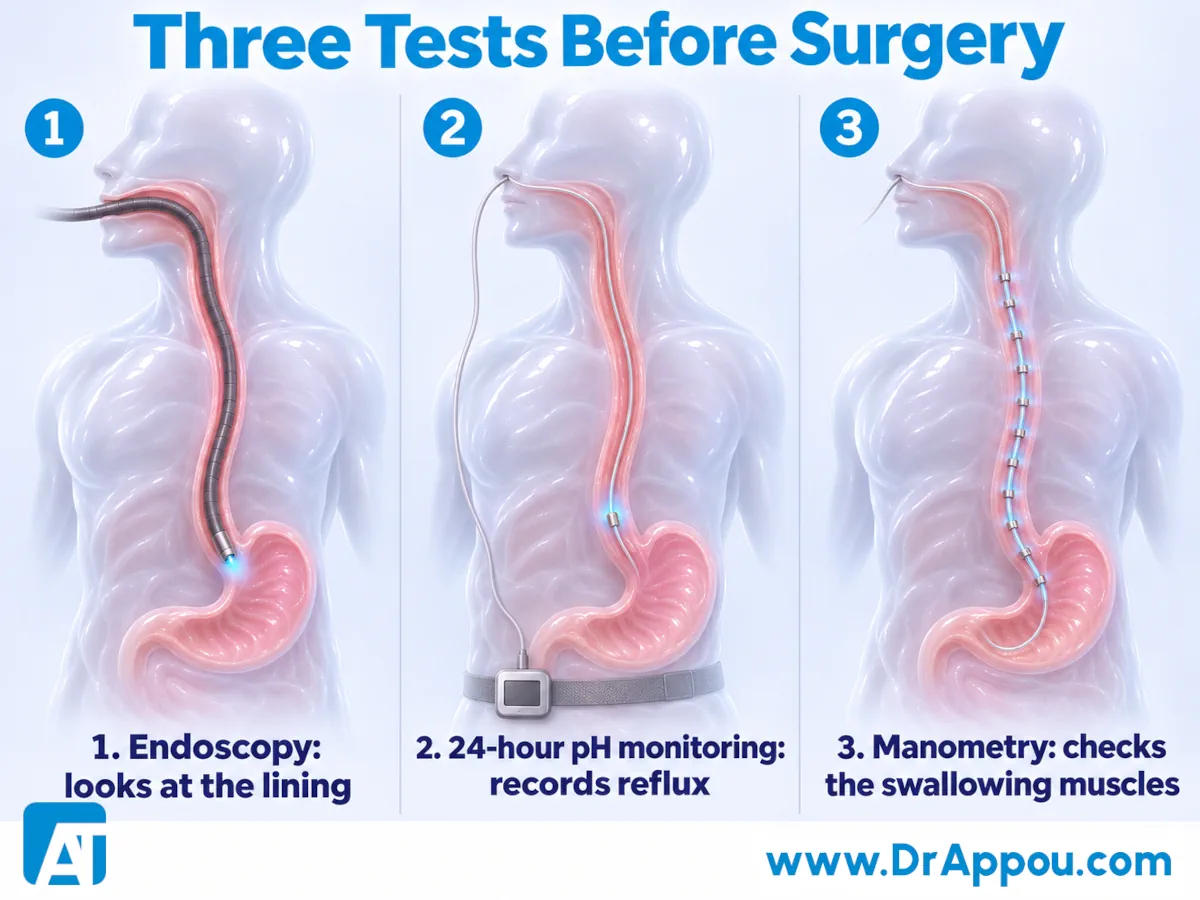
All three tests are available at Fakeeh University Hospital. Testing matters: in a US trial of people whose heartburn did not respond to PPIs, careful testing found reflux to be the cause in only 78 of 366 (about 1 in 5). In those 78, keyhole anti-reflux surgery relieved heartburn more often than further medication. [4]
I am thorough about manometry because a motility disorder can sit behind symptoms such as chest pain, bloating or nausea, and it only shows up on this test.
“Manometry gives important information about if there is any problem with the motility of the oesophagus. In any case, it is important to look for any motility-related problems before subjecting patients to fundoplication.”
Dr. Appou Tamijmarane
The three tests point to one of three outcomes: surgery is appropriate, surgery is not appropriate, or more investigation is needed first.
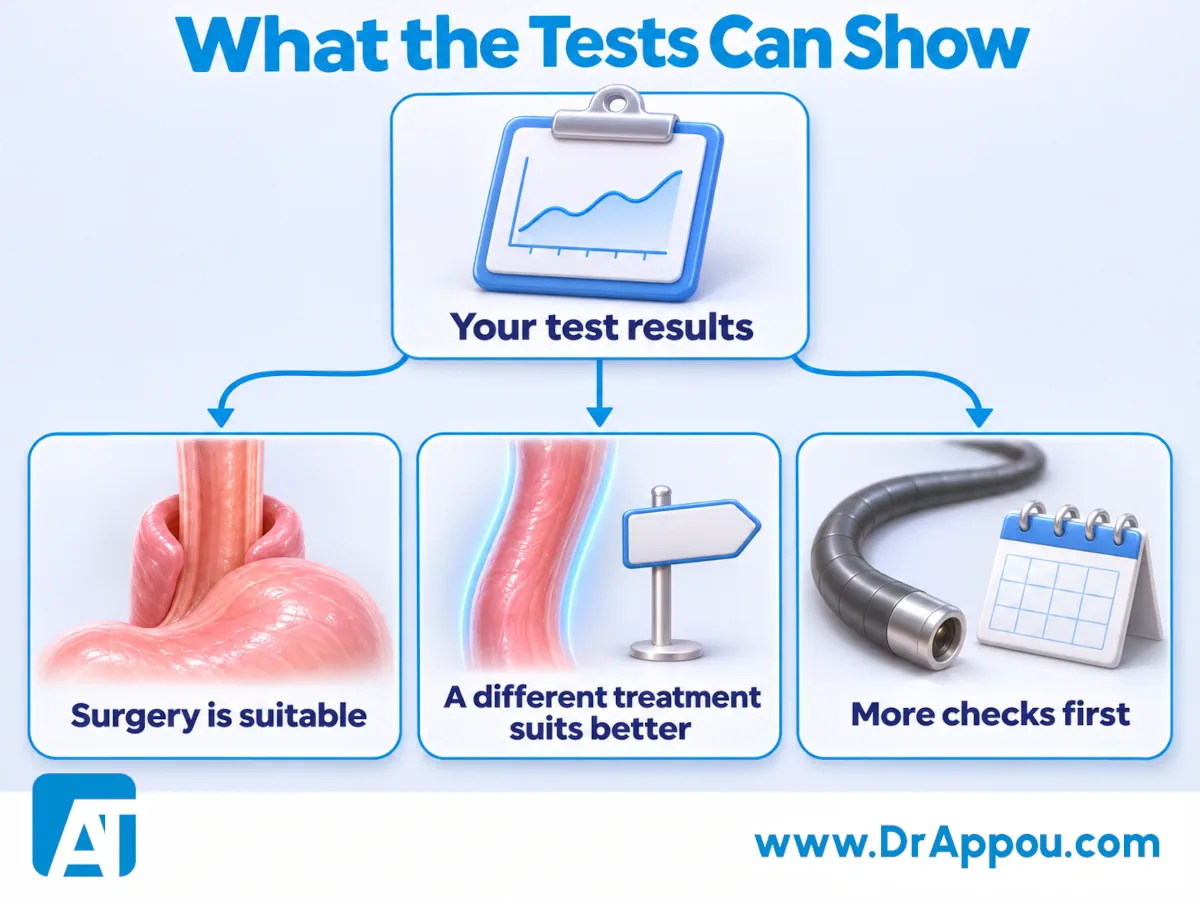
pH testing confirms significant reflux, manometry shows the oesophagus moves normally, and you are fit for keyhole surgery. This is when I discuss fundoplication in detail.
Manometry may show a motility disorder, such as achalasia, diffuse oesophageal spasm (sometimes called corkscrew oesophagus) or nutcracker oesophagus. These cause symptoms very like reflux, including chest discomfort, difficulty swallowing and food sticking, but they need a completely different treatment. If I find one, a fundoplication is not the right operation for you, and I will recommend the treatment that suits your condition instead.
“Such patients who have been found to have various types of motility issues need to be addressed on their own merits. And some of them may need various types of medical treatment to relieve the spasms in the oesophagus, sometimes oesophageal dilatation with the pneumatic balloon or [botulinum toxin] injection, and sometimes they may need a surgery such as Heller’s cardiomyotomy with partial fundoplication.”
Dr. Appou Tamijmarane
Heller’s cardiomyotomy is a different operation from reflux surgery. Choosing the right treatment for the right condition is exactly why manometry comes first.
If the endoscopy shows changes that may be Barrett’s oesophagus, a change in the lining of the lower oesophagus after long-term acid damage, specialist gastroenterology review and a programme of regular endoscopy checks come first, before any surgical decision. [6]
I usually perform a keyhole Toupet fundoplication, a partial 270-degree wrap, because in my experience it causes less bloating and difficulty swallowing than a full Nissen wrap.
Patients are often told they need “a fundoplication” without being told that the technique matters. Both types wrap the top of the stomach around the lower oesophagus to strengthen the valve. A Nissen wraps all the way round (360 degrees) and has historically been the most widely performed. A Toupet covers 270 degrees behind the oesophagus, allowing more natural movement when swallowing, and practice has been moving towards it for many years.
“I prefer to do Toupet repair as it provides posterior 270-degree cover, rather than a full 360-degree cover (Nissen). In my experience, Nissen causes more bloating, difficulty in swallowing, and increased flatulence, and hence I prefer doing the Toupet procedure.”
Dr. Appou Tamijmarane
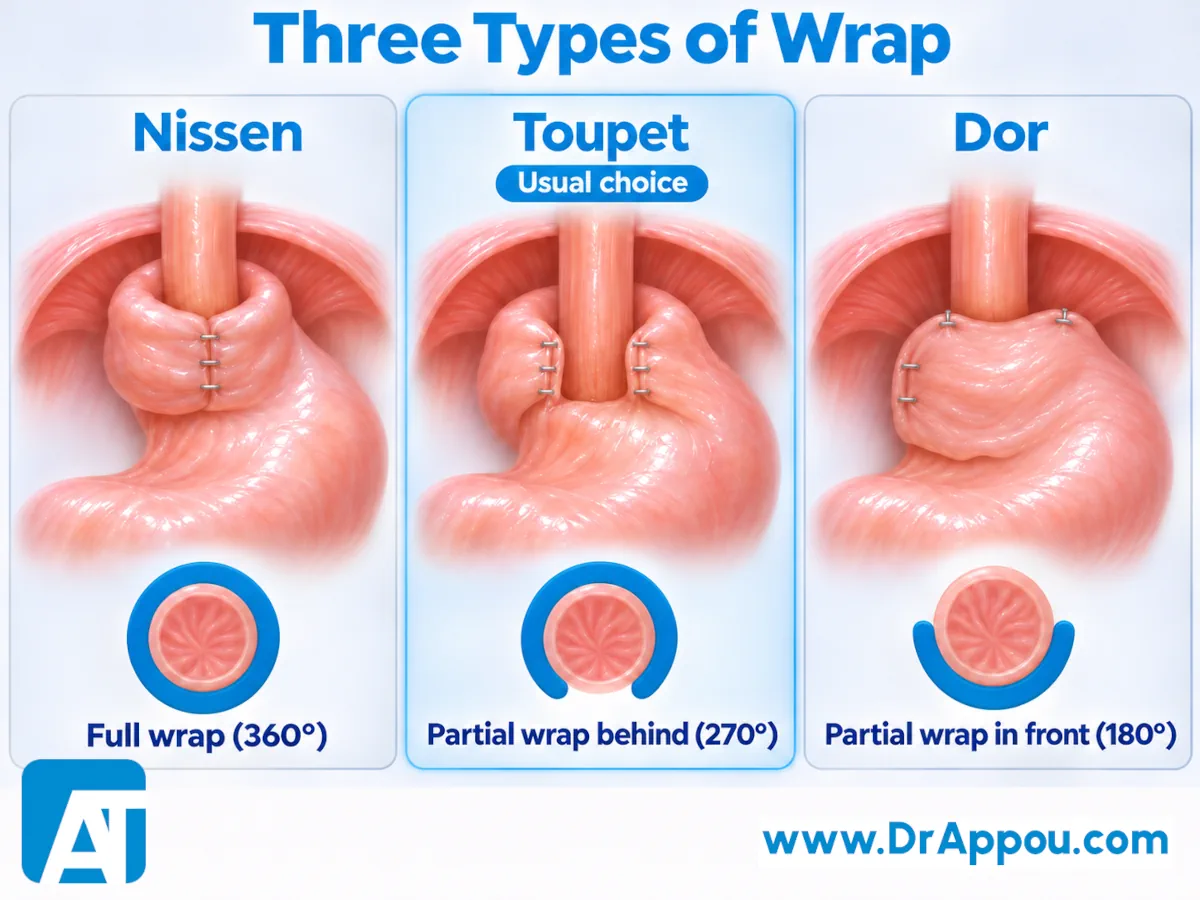
Published evidence supports this: in a review of randomised trials, both wraps controlled reflux similarly, but the partial wrap was linked to less long-term difficulty swallowing and fewer problems belching. [5] A Toupet is my usual operation, but it is not right for everyone: for some patients, a Nissen or a Dor wrap (a partial wrap across the front of the oesophagus) suits their anatomy or test results better, and I perform these too. I do not present my preference as a universal verdict: surgeons with different training will have different experiences. If you are seeing another surgeon, it is always worth asking which technique they recommend for you and why.
I perform the operation by keyhole (laparoscopic) surgery at Fakeeh University Hospital. It usually takes one to two hours, and most patients go home the next day, all being well. For carefully selected patients, the results last: in a large European trial, most patients were still in remission five years after keyhole anti-reflux surgery. [7] Before any decision, I go through the benefits and risks in detail with you, and with your family if you wish.
“I do think actually giving as much information as possible to the patient and the family beforehand prepares them well to face any problems that may arise as a result of the intervention.”
Dr. Appou Tamijmarane
If you have had reflux surgery and your symptoms have not settled, the starting point is a full reassessment, including manometry if it has not been done before.
Sometimes symptoms do not settle after a fundoplication of either type, or new symptoms appear. In many of these cases, the operation itself was technically sound, and the answer lies in a motility disorder, which is very hard to detect without manometry and can easily be mistaken for reflux. This is why I insist on manometry before operating, and why I encourage anyone considering a fundoplication to ask whether it has been done.
“Seeking a second opinion is an appropriate thing to do from both the patient and doctor’s point of view. I have seen quite a few patients in my practice seeking second opinion about surgeries they’ve been advised to go through by another surgeon in another facility or even in our own facility. Sometimes a patient seeks a second opinion if they feel that they are having a problem while recovering after an operation.”
Dr. Appou Tamijmarane
I see patients at Fakeeh University Hospital, Dubai Silicon Oasis, face to face or online, in English or Tamil.
Fakeeh University Hospital is in Dubai Silicon Oasis, close to Academic City, International City, Mirdif and Dubailand. A translator can be arranged for other languages, and free parking is available.
To book a consultation, use the Okadoc booking system or call the Fakeeh University Hospital booking line on +971 4 414 4444. If you would like to speak with me before booking, you can message me on WhatsApp.
In summary
References
The figures on this page are drawn from international clinical guidelines and peer-reviewed studies, listed in the references above. They describe results reported in published research; your own risks and options will be discussed with you at your consultation.
Signs PPIs are not working · The surgical evaluation · What tests might find · Why Toupet · After failed surgery · Book a consultation · FAQs
Medical Disclaimer
This article is for general education and does not replace medical advice, diagnosis or treatment. Individual treatment and surgical decisions must be made with a qualified healthcare professional after a full clinical assessment. If you vomit blood, pass black stools, have severe chest pain or any of the warning signs on this page, seek emergency care promptly. Dr. Appou Tamijmarane is licensed by the Dubai Health Authority (DHA License No: 50530660-001) and practises as a Consultant General Surgeon at Fakeeh University Hospital, Dubai Silicon Oasis, UAE. Patient testimonials referenced elsewhere on this website are published with consent.